

Cancer caused by infectious diseases are preventable
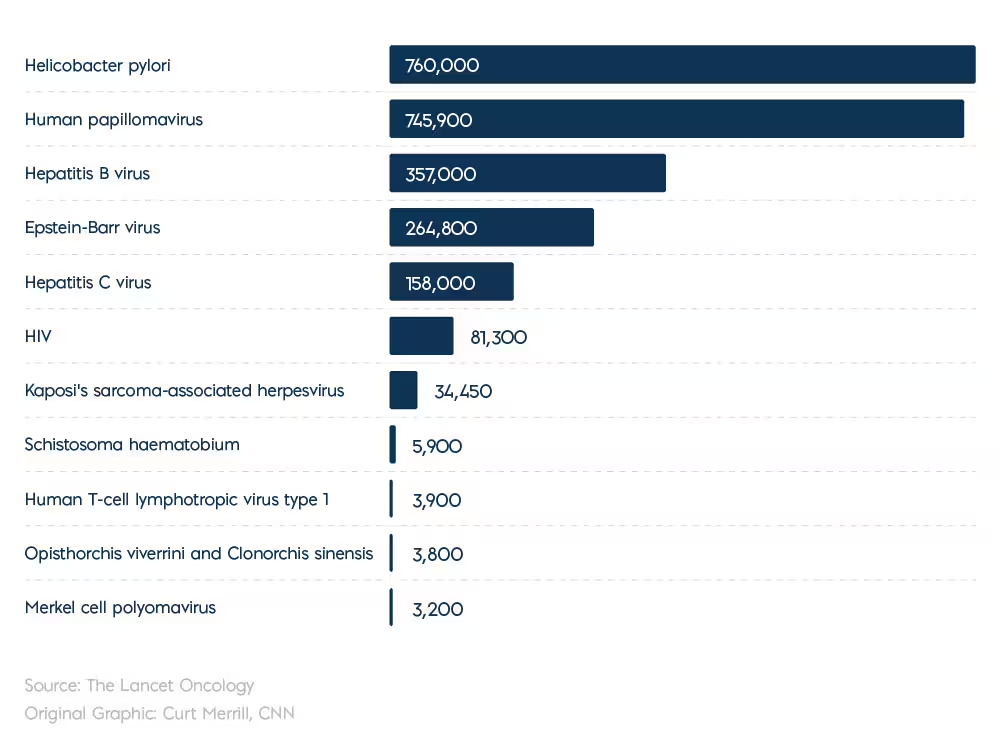
A new global analysis published in The Lancet Oncology estimates that 2.3 million new cancer cases in 2024
were attributable to infectious agents. H. pylori was associated with the largest number of cases,
approximately 760,000 worldwide, more than any other infectious agent included in the analysis. The finding
reinforces an important point for clinicians: some cancer-prevention opportunities begin with identifying and
treating an infection.
For gastroenterologists and primary care teams, H. pylori is a particularly actionable example. The bacterium
is a recognized cause of gastric cancer and is also associated with peptic ulcer disease and other
gastrointestinal conditions. A recent South Korean population-based study found that individuals who
received H. pylori eradication treatment had lower long-term colorectal cancer incidence and mortality than
expected in the general population. The findings suggest that treating H. pylori may provide benefits beyond
gastric cancer prevention, potentially including reduced colorectal cancer (CRC) risk. However,
observational design cannot establish causation, so further prospective studies are needed.
Although the causal relationship between H. pylori infection and gastric cancer is well established, infection
can be overlooked. Approximately 30–36% of people in the United States are estimated to be infected, yet
many have no symptoms or only nonspecific gastrointestinal symptoms. The lack of routine testing means
that many infections may go undiagnosed. A prevention-focused approach therefore depends on selecting
appropriate patients for testing, using a reliable method to identify active infection, and confirming
eradication after treatment.
Turning awareness into action
The new publication linked H. pylori testing and treatment with infection-related cancer prevention and
connect clinicians’ everyday decisions—evaluating dyspepsia, investigating ulcer disease, assessing
relevant risk factors, and confirming treatment success—to a cancer prevention goal.
When evaluating patients for potential H. pylori infection, there are three questions to be considered:
• Who should be tested? Consider the patient’s symptoms, history, local guidance, family history, prior
ulcer disease, and other risk factors.
• Does the test identify active infection? The 2024 American College of Gastroenterology (ACG) guideline
emphasizes using testing methods that detect active H. pylori infections such as urea breath testing,
stool antigen testing, or biopsy-based testing—rather than relying on serology, which may remain
positive after the infection has cleared and cannot reliably distinguish current infection from past
exposure.
• Has eradication been confirmed? A post-treatment test-of-cure helps distinguish successful treatment
from persistent infection and supports appropriate patient management.
Partnership to strengthen prevention in everyday practice
The global cancer burden associated with infections is substantial, but the clinical response can begin at the
point of care. For practices caring for patients with gastrointestinal symptoms or risk factors for H. pylori,
now is an opportunity to review whether current workflows consistently address active infection and test-of
cure needs.
Both stool antigen test and urea breath test can provide a noninvasive way to assess active H. pylori
infection and to confirm eradication after treatment. For many practices, a streamlined workflow can
support patient care, reduce burdens associated with invasive procedures and make testing easier to
incorporate into routine care. Test selection and timing should follow up-to-date ACG guidelines.
Meridian can work with GI and primary care teams to discuss testing needs, workflow requirements, and
how BreathID and other H. pylori diagnostic solutions may fit within their practice. Contact Meridian to
explore a prevention-focused H. pylori testing strategy for your organization today.
References
Jung YS, Jeon S, Park B, Moon CM. Preventive Effect of Helicobacter pylori Treatment on Colorectal Cancer
Incidence and Mortality. Journal of Gastroenterology and Hepatology. 2026;41(8):2356–2364.
Rumgay H, Georges D, Huang Y, et al. Global burden of cancer attributable to infections in 2024: a worldwide
incidence analysis. The Lancet Oncology. 2026;27:1237–1248.
Shah SC, et al. Helicobacter pylori Burden in the United States According to Individual Characteristics and
Geography. Clinical Gastroenterology and Hepatology. 2024. cghjournal.org



